
|
#1
●
07-04-2024, 07:18 PM
|
 These are the rooms Poster Rank:26 of ruin. Join Date: Sep 2014 Posts: 54,008 54,008Posts 87,664Thanked 30,403Quoted 145Mentioned 0Contrib. |
|
Facial Lesions
A 52-year-old Syrian presented to the dermatology department at Hatay Mustafa Kemal University with complaints of facial lesions and purulent rhinitis for 3 months. He also had vitiligo for 20 years. The patient had no history of smoking, alcohol consumption or systemic disease. Dermatologic examination revealed crusted and infiltrated granulomatous plaques on the anterior upper surface and side of the nose, cheeks and lower and upper lips with purulent discharge [Figure - 1]. The lesions had affected the anterior nasal septum and columella. Nasal examination showed mucopus in the nasal cavity, loss of tissue on the columella and cartilage necrosis on the anterior nasal septum and consequently, loss of tip support. In addition, depigmented macules of vitiligo were noted on the face and extremities. General physical examination was normal. Laboratory tests revealed that the white blood cell count was 20.86 × 10[3]/µL (4–10 × 10[3]/µL), sedimentation rate was 100 mm/h (0–12 mm/h) and C-reactive protein levels were 86.6 mg/dl (0–5 mg/dl). Other laboratory tests were within normal limits. HIV and hepatitis C tests were negative. Culture from the purulent discharge grew Pseudomonas aeruginosa. The patient was treated with levofloxacin, 750 mg by intravenous infusion for 10 days. Following treatment, suppuration decreased and granulomatous lesions became more visible. Histopathologic examination revealed acanthosis with pustule formation on the surface of follicular epithelium and a dense, diffuse inflammatory infiltrate of lymphocytes, many plasma cells and epithelioid cells in the papillary and reticular dermis [Figure - 2]a and [Figure - 2]b. These findings were suggestive of mucocutaneous leishmaniasis but no parasite was seen. Leishmania amastigotes were found in the tissue smear prepared from the edge of the lesion . On the basis of history, clinical and histopathological findings and skin smear results, mucocutaneous leishmaniasis was diagnosed. The patient was treated with systemic meglumine antimoniate, 20 mg/kg/day intramuscularly, in 2 divided doses for 30 days. The lesions improved dramatically 1 month after the treatment []. Mucocutaneous leishmaniasis is a serious and potentially life-threatening form of the disease. It is often perceived as a New World disease almost only found in South America but rarely seen in the Old World. Mucosal manifestations can be seen in about 5–20% of cutaneous leishmaniasis. The lag period between developing cutaneous lesions and the later onset of mucosal involvement ranges from months to years. The nasal mucosa is the most commonly affected area and involvement of other mucosal sites is rare.[1] In patients with nasal mucosal involvement, the disease can begin with non-specific symptoms such as persistent nasal stuffiness, discharge, discomfort or epistaxis.[2] Our patient also presented with purulent nasal discharge. Secondary infection is reported in 54.2% of cases and is usually caused by Staphylococcus aureus.[3] In our case, Pseudomonas aeruginosa was the cause and the patient responded well to treatment with levofloxacin. Atypical aspects such as extensive and destructive lesions, have often been found in cases of leishmaniasis associated with HIV infection.[4] In our case, although HIV tests were negative, a massive and disfiguring central face involvement occurred in a short time. The clinching evidence for a diagnosis of mucocutaneous leishmaniasis is the demonstration of Leishmania parasites. On biopsy, amastigotes can be seen in only 25% of the skin lesions.[5] In our case, the histopathological findings were suggestive of mucocutaneous leishmaniasis but amastigotes could not be identified. However, amastigotes were detected by direct microscopic examination. In mucocutaneous leishmaniasis, long-term systemic treatment with pentavalent antimonials or amphotericin B is required.[5] In view of the extent and severity of the disease, our patient was treated with intramuscular meglumine antimoniate, 20 mg/kg/day for 30 days. Because of the fairly early diagnosis, appropriate treatment and the absence of any underlying primary immunodeficiency, our patient had a good prognosis. In addition, the response to treatment was dramatic. Early diagnosis and appropriate treatment of mucocutaneous leishmaniasis is essential as there is a risk of extension of the disease and destruction of facial structures such as the nose, palate and buccal mucosa with potentially fatal pharyngeal and laryngeal involvement. 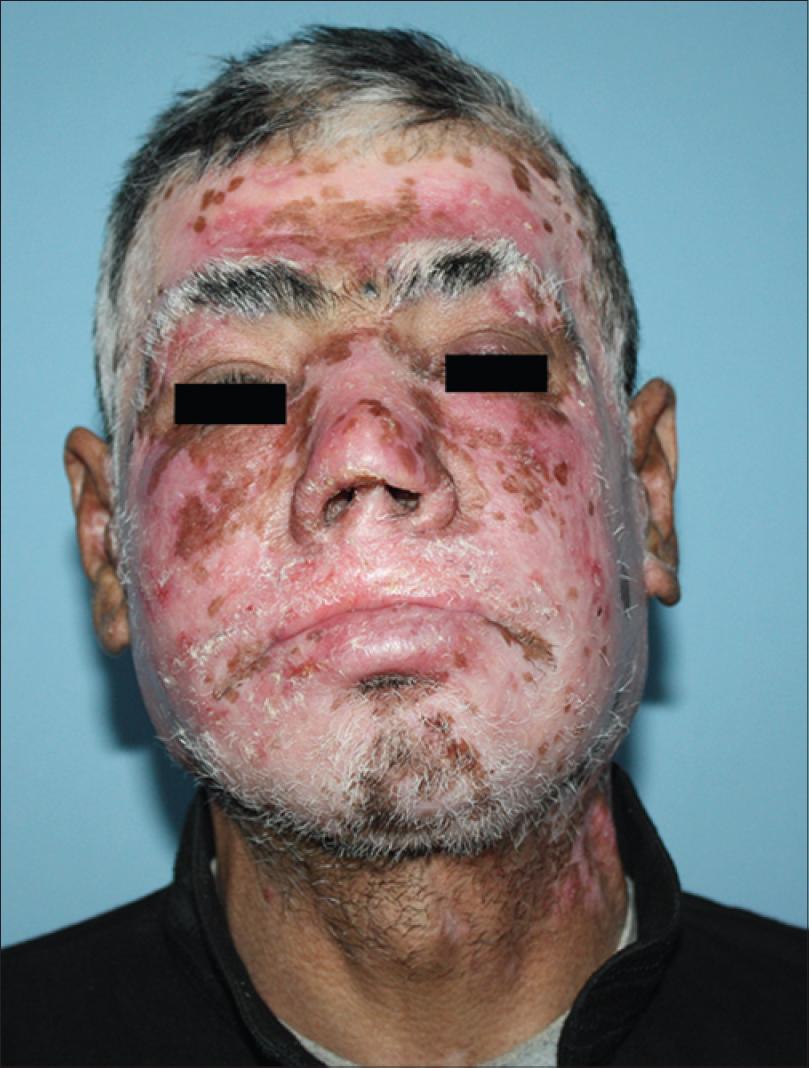 · 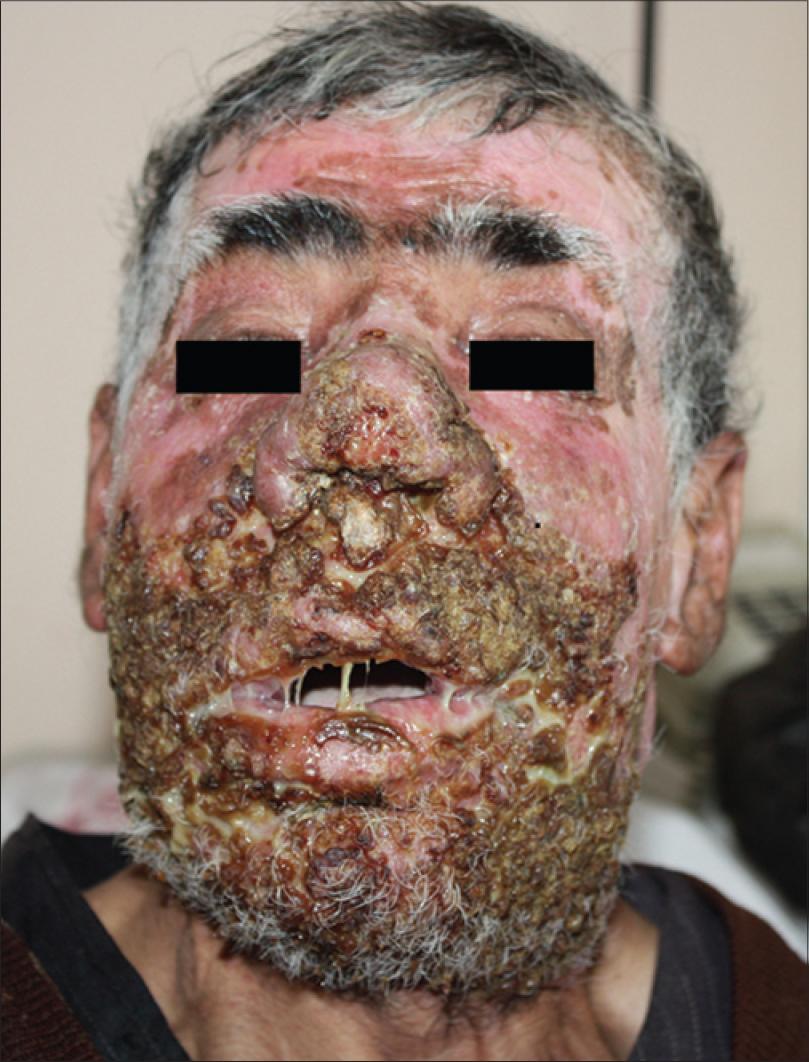 · |


