
|
#1
●
07-29-2024, 05:38 PM
|
 These are the rooms Poster Rank:26 of ruin. Join Date: Sep 2014 Posts: 54,008 54,008Posts 87,658Thanked 30,403Quoted 145Mentioned 0Contrib. |
|
Crush Injury
A 34-year-old male paramedic was involved in a motor vehicle accident and admitted for diagnosis and surgical treatment. He sustained a crush injury to his right hand with significant muscle damage, including multiple fractures and dislocations, an avulsion injury of the flexor tendons, and amputation of the distal phalanx of the little finger (Fig. 1). Emergency reconstructive surgery was performed. The distal phalanx of the fifth finger did not satisfy the minimum conditions for replantation, and the presence of debris in the wound and an unviable aspect of the thenar musculature were also noted. The wound was then abundantly washed with saline, and debridement was performed to clean the wound from unviable tissue. The interphalangeal joint dislocations of the middle and little fingers were reduced and fixed using Kirschner wires under image intensifier guidance. Tenorrhaphy of the distal flexor digitorum profundus stumps and proximal flexor digitorum superficialis (FDS) stumps of the middle and ring fingers was performed, followed by transosseous suturing of the distal FDS stump to the middle phalanx of the avulsed little finger. Grafting of the distal FDS stump of the little finger to the proximal FDS stump of the ring finger was achieved with tendon transfer. The wound was closed using a plane suture as satisfactorily as technically possible (Fig. 2). Volume replacement therapy, pain medication, broad-spectrum antibiotics, and nutritional support were initiated as per the service’s routine. The wound showed progressive tissue damage, manifesting mainly as a change in the color of the skin associated with progressive edema (Fig. 3). Despite the delayed start of HBOt, the color in some of the ischemic and hypoxic superficial tissues improved within the first days of adjunct treatment (day 6), after only three HBOt sessions. In addition, the posttraumatic edema also improved markedly with HBOt (Fig. 4). The lesion progressed to soft tissue necrosis in the thenar region with superficial spreading towards the base of the fingers (Fig. 5). Over the ensuing days, occlusive dressings were changed daily and unviable tissue was removed, eventually revealing wet necrosis and infection in the middle phalanx of the little finger (Fig. 6). The patient was taken to the operating room for amputation of the distal phalanx of the little finger, and a thenar skin flap was taken from the right forearm (Fig. 7). Concurrently, an early rehabilitation program was initiated with an excellent functional outcome and full restoration of hand function at the end of treatment, despite the loss of the distal and middle phalanges of the little finger (Fig. 8). Informed consent for publication of the research details and clin*ical images was obtained from the patient. 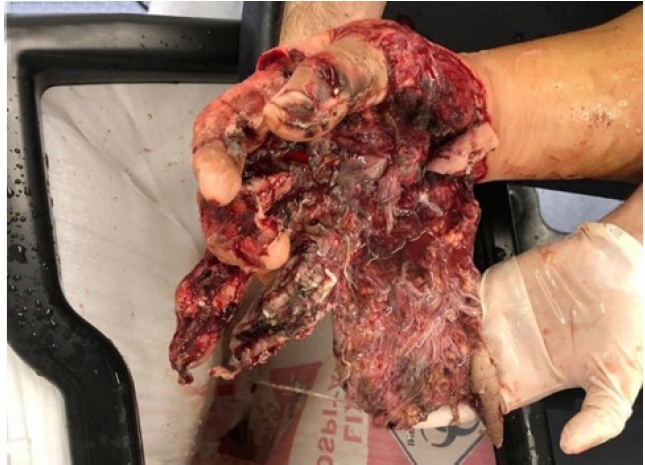 · 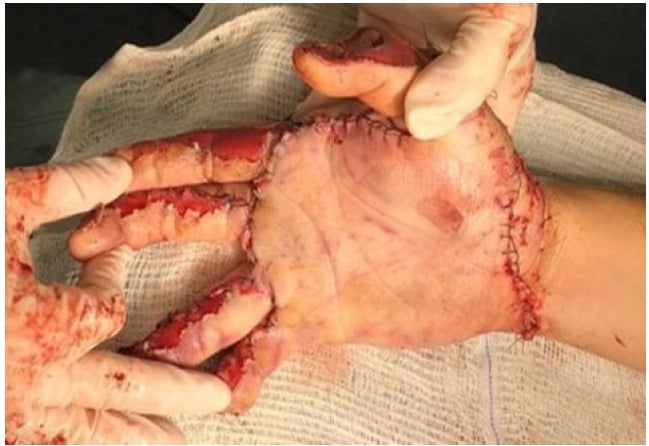 · 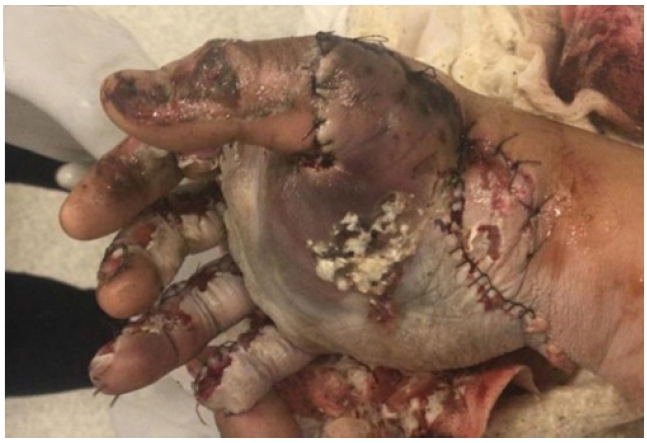 · 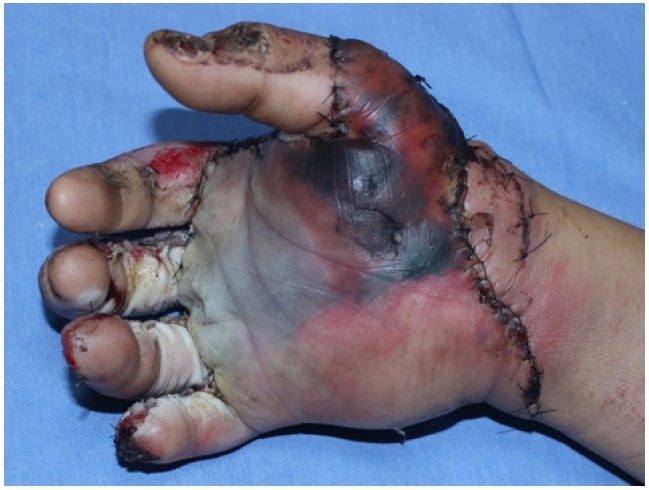 · 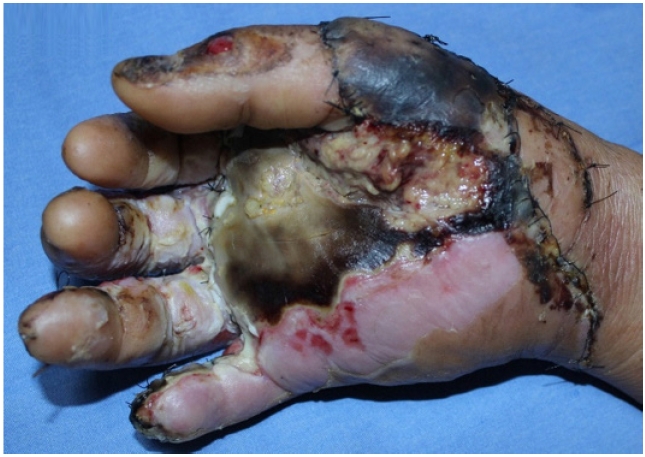 · 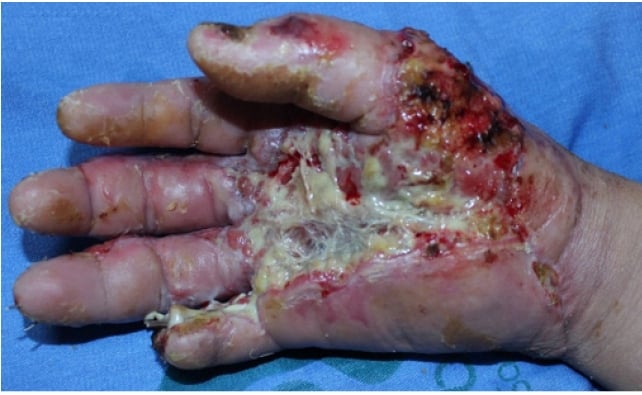 · 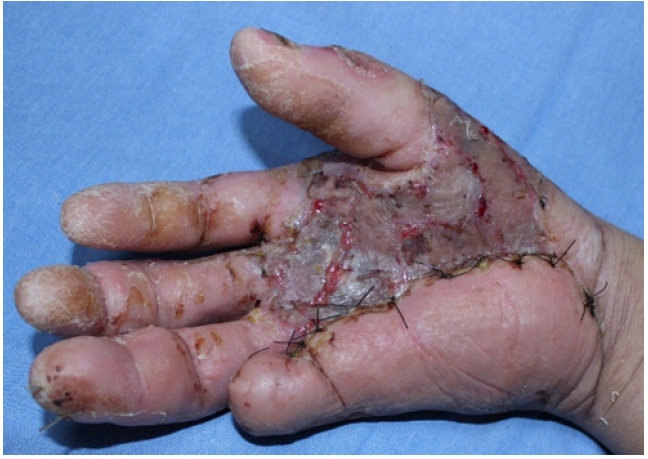 · 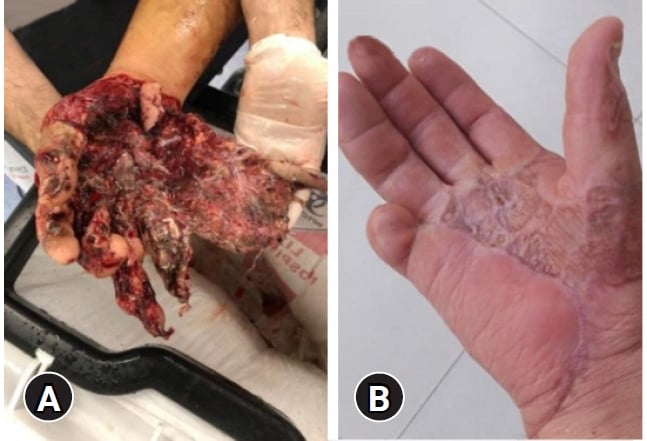 · |
|
#3
●
07-30-2024, 12:15 AM
|
| My Rank: LANCE CORPORAL Poster Rank:3136 Female [real] Join Date: Oct 2013 Posts: 122 122Posts 195Thanked 30Quoted 1Mentioned 0Contrib. |
|
Re: Crush Injury
Holy shit, that recovery is amazing! Modern medicine is fucking awesome.  |
|
#4
●
07-30-2024, 03:57 AM
|
 ✝Mudderator from Hell✝ Poster Rank:10 e-mail Join Date: Oct 2006 Posts: 96,631
Contributions: 901
96,631Posts 543,004Thanked 10,364Quoted 479Mentioned 901Contrib. |
|
Re: Crush Injury
too bad about the necrosis or else he still had his entire pinky functional as well.
|
|
#5
●
07-30-2024, 10:58 PM
|
 My Rank: STAFF SERGEANT Poster Rank:876 Male Join Date: Jun 2011 Posts: 864 864Posts 2,301Thanked 227Quoted 0Mentioned 0Contrib. |
|
Re: Crush Injury
Hard to believe that that original mess of tissue healed and he has function again in that hand.   But I agree with TyrRoo that some of the photos were difficult to view.  |


